
PATIENT INFORMATION
Sinusitis (Rhinosinusitis)
Sinusitis is inflammation of the lining of the nose and sinuses; today it is usually called rhinosinusitis, because inflammation of the sinuses is almost always accompanied by inflammation of the nasal lining. Its short-term (acute) and long-term (chronic) forms differ in their causes and management. This page explains what sinusitis means, which symptoms suggest it, what is done in the ENT assessment, when imaging is needed and the principles of treatment.
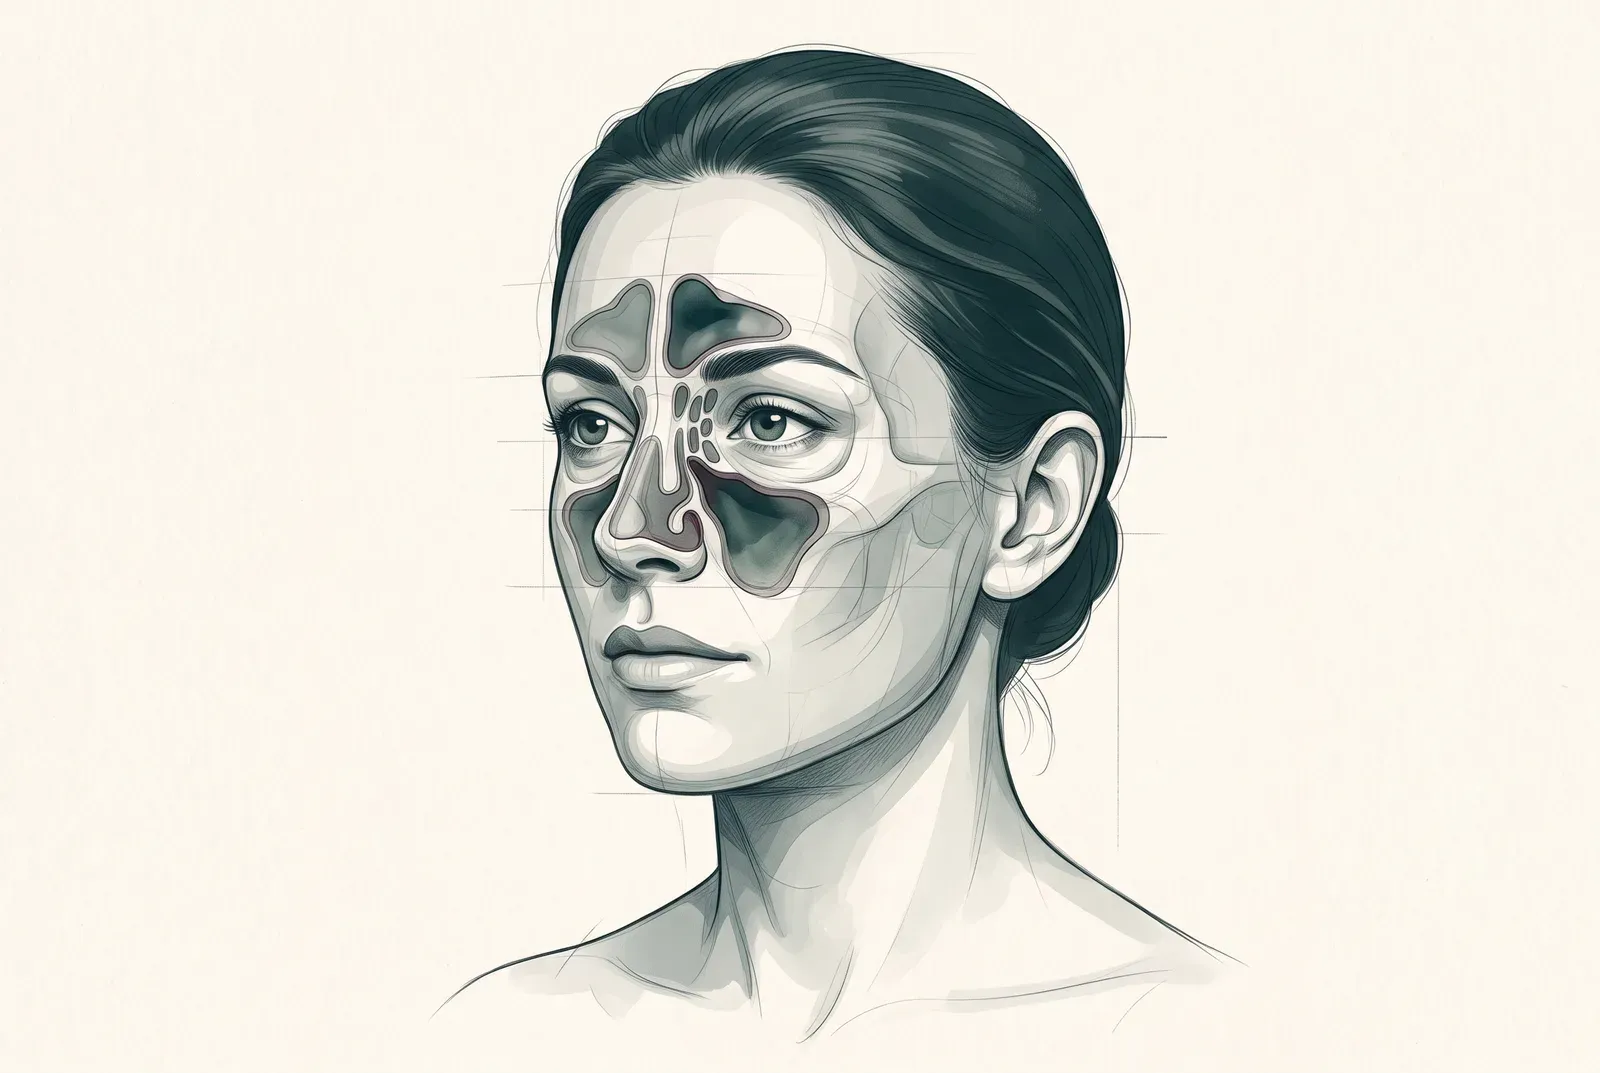
What is sinusitis?
The sinuses are air-filled cavities surrounding the nasal cavity and opening into the nose. Because the sinus lining is a continuation of the nasal lining, sinusitis is almost always seen together with inflammation of the nasal lining; current guidelines therefore use the term rhinosinusitis.
In the guidelines, the diagnosis rests on symptoms and examination findings. The typical symptoms are nasal obstruction and nasal discharge or postnasal drip; these may be accompanied by facial pain or pressure and a reduced sense of smell. The combination of these symptoms is what matters for the diagnosis; headache alone, or facial pressure alone, does not mean sinusitis.
The difference between acute and chronic sinusitis
Acute rhinosinusitis is a short-course illness; the current AAO-HNSF adult sinusitis guideline (2025) defines it as lasting up to four weeks. The great majority of cases are due to viral upper respiratory infections such as the common cold and settle on their own. According to the same guideline, two basic patterns suggest bacterial sinusitis (acute bacterial rhinosinusitis): symptoms persisting without improvement for at least ten days after onset, or symptoms worsening within ten days after an initial improvement (“double worsening”). This distinction matters because it influences the treatment approach. Findings such as high fever, swelling around the eye or marked deterioration of the general condition are separate from these diagnostic patterns and belong to the urgency assessment described in the warning section above.
Chronic rhinosinusitis is a persistent or fluctuating condition in which symptoms have lasted for at least twelve weeks. Guidelines differ in how they name presentations lasting between four and twelve weeks (the European guideline, EPOS 2020, treats presentations shorter than twelve weeks as acute); this page distinguishes only short-course (acute) presentations from chronic ones lasting at least twelve weeks. The cause of chronic rhinosinusitis is not a single infection but an ongoing inflammatory process in the sinus lining. Nasal polyps can develop as one form of this process; chronic rhinosinusitis with and without polyps is assessed separately. Recurrent acute episodes are a further, distinct form of complaint.
What is done in the ENT assessment?
The assessment begins with a detailed history: the duration and course of the symptoms, the nature of the obstruction and discharge, facial pain or pressure, changes in the sense of smell, allergic complaints, previous nasal surgery and the medicines being used.
During the examination the inside of the nose is inspected with a light; where needed, nasal endoscopy is performed with a thin optical instrument. Endoscopy makes it possible to see directly whether inflammatory discharge, swelling of the lining or polyps are present in the area where the sinuses open into the nose, and it is particularly important in assessing chronic presentations.
If the history suggests an allergic background, allergy assessment may be considered. In chronic and recurrent presentations, accompanying conditions such as asthma are also explored, because inflammation of the upper and lower airways frequently occurs together.
Is a CT scan needed for every case of sinusitis?
No. In acute, uncomplicated sinusitis, imaging is not routinely required; the diagnosis is made from the history and examination. Guidelines do not recommend imaging in acute sinusitis unless a complication is suspected or the course is unusual.
A sinus CT scan is meaningful when its result would change treatment: chronic rhinosinusitis that does not respond to appropriate medical treatment, surgical planning, suspected complications and findings suggesting a growth inside the nose are the main examples. CT findings do not always match the symptoms; thickening of the lining can be seen even in people without symptoms. CT is therefore interpreted together with the examination, not instead of it.
How is the treatment approach decided?
Treatment is planned according to whether the condition is acute or chronic and to the cause identified.
Acute sinusitis of viral origin usually resolves on its own; during this period saline nasal irrigation and symptom-directed supportive measures are used. Antibiotics are not required for every case of acute sinusitis. Even when the bacterial pattern is met, this does not by itself mean that antibiotics are needed: the 2025 AAO-HNSF guideline recommends watchful waiting without antibiotics as an initial option for bacterial sinusitis without signs of complication, provided that follow-up is assured; antibiotics may be the initial choice or the option used if symptoms do not improve. Which approach is appropriate, and for how long any antibiotic is used, is decided by the physician.
In chronic rhinosinusitis the basis of treatment is intranasal corticosteroid treatment and regular nasal irrigation; in presentations with polyps and where there is an allergic background, additional options are considered. Where complaints persist despite appropriate medical treatment, endoscopic sinus surgery may be considered. Surgery does not replace medical treatment; it aims to widen the pathways through which the sinuses open into the nose and to make subsequent medical treatment more effective. Whether it is appropriate is decided by assessing the examination and CT findings together with the response to treatment.
This page deliberately contains no drug names, doses or treatment durations; treatment is planned individually by the physician.
Frequently asked questions
Is every headache a sign of sinusitis?
No. Headache has many causes, and headache alone is not sufficient for a diagnosis of sinusitis. The picture that suggests sinusitis is a combination of symptoms in which nasal obstruction and discharge predominate and facial pressure and a reduced sense of smell may be present. Causes of pain such as migraine are frequently mistaken for sinusitis; the distinction is made by examination.
Are antibiotics essential in sinusitis?
No. The great majority of acute sinusitis is viral and resolves without antibiotics. Symptoms persisting without improvement for at least ten days, or worsening within ten days after an initial improvement, suggest bacterial sinusitis; but even this pattern does not by itself require antibiotics. The current guideline accepts watchful waiting without antibiotics as an initial option for bacterial sinusitis without signs of complication when follow-up is assured. The decision is made by the physician together with the examination.
Does chronic sinusitis go away completely with surgery?
Chronic rhinosinusitis is an ongoing inflammatory disease; surgery is a step that makes its treatment easier and does not carry a promise of a permanent cure on its own. Regular nasal care and continued medical treatment are usually needed after the operation. The expected benefit and the follow-up plan are discussed with the physician according to the individual presentation.
How are nasal polyps related to sinusitis?
Nasal polyps are benign swellings that develop from the sinus lining in one form of chronic rhinosinusitis; they present with a reduced sense of smell and two-sided obstruction. The treatment and follow-up of chronic rhinosinusitis with polyps can differ from the form without polyps, which is why endoscopic assessment matters.