
PATIENT INFORMATION
Neck Lump (Swelling in the Neck)
A neck lump is a swelling or firmness noticed in the neck that is not normally present. Its possible causes depend on age and clinical context: enlarged lymph nodes due to infection, lesions arising from the thyroid or salivary glands, and developmental cysts are among the possible causes. A neck lump that cannot be explained by an infection, has been present for two weeks or longer, is not clearly shrinking, or whose duration is uncertain should nevertheless be assessed without delay, particularly in an adult. This page explains the possible causes of a neck lump, which features bring the assessment forward, what is done in the ENT and head-and-neck examination and the general principles of further investigation.
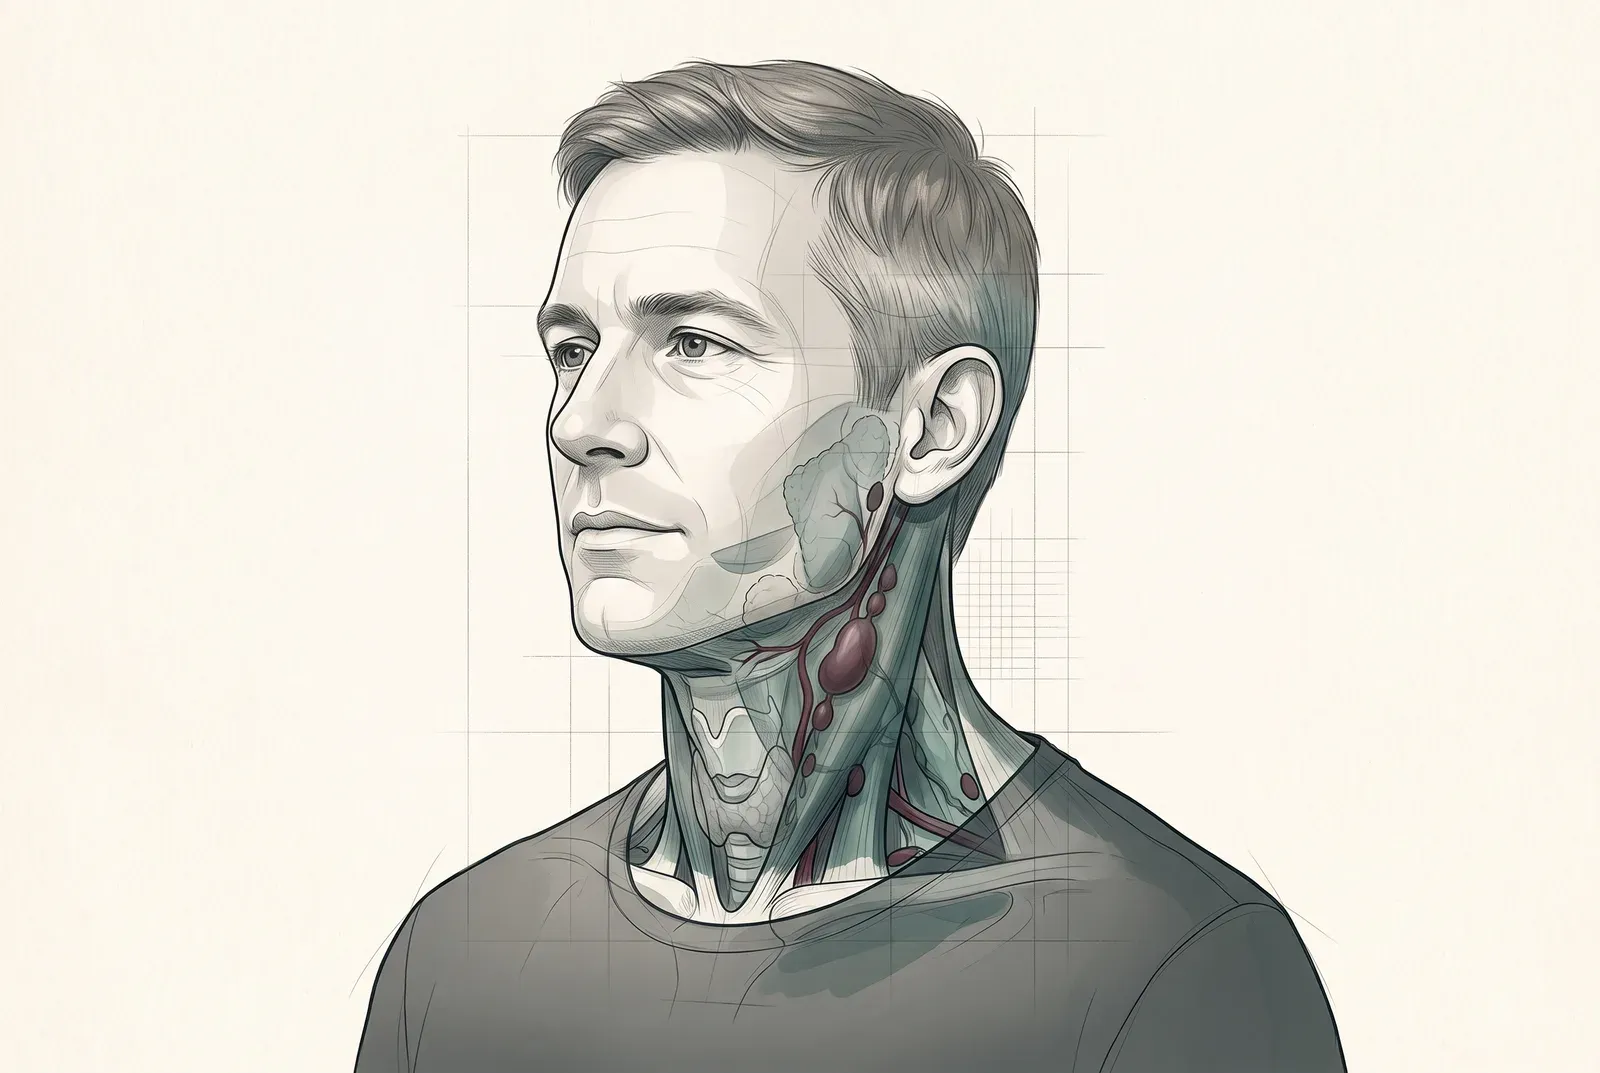
What does a neck lump mean?
The neck contains lymph nodes, the thyroid gland, the salivary glands, blood vessels, muscles and some remnants of structures from development before birth. Swellings arising from any of these structures may be noticed as a neck lump; the location, consistency, mobility and duration of the lump give important information about the possible causes.
The distribution of possible causes changes with age. In children and young adults, enlarged lymph nodes due to infection and developmental cysts feature more prominently in the differential diagnosis; the guideline on which this page is based, by contrast, concerns neck masses in adults and calls for a more cautious diagnostic approach to a persistent adult neck lump. According to that guideline, an adult neck lump that cannot be explained by an infection, has been present for two weeks or longer, or whose duration is uncertain is a finding that needs to be assessed until its cause has been determined; factors such as smoking or alcohol use bring that assessment forward still further. This does not mean the lump is malignant; it means that assessment should not be postponed.
Possible causes
Neck lumps fall into the following main groups according to the structure they arise from:
- Inflammatory and infection-related lymph node enlargement (commonly called swollen glands): Lymph nodes that enlarge during throat, dental and upper respiratory infections, are usually tender and shrink once the infection has passed. Some specific infections, such as tuberculosis, can also cause lymph node enlargement.
- Swellings arising from the thyroid: Enlargement of the whole thyroid gland (goitre) or thyroid nodules; they lie in the lower front of the neck and move on swallowing.
- Swellings arising from the salivary glands: Inflammation of the salivary glands in front of the ear and under the jaw, salivary stones, or tumours of these glands.
- Congenital cysts and developmental lesions: Thyroglossal duct cysts in the midline of the neck and branchial cleft cysts at the side of the neck; they are usually noticed in childhood or young adulthood, often after an infection.
- Lesions arising from blood vessels and nerves: Lesions that develop from the vessels and nerves of the neck.
- Skin and subcutaneous lesions: Superficial benign lesions such as lipomas (fatty lumps) and skin cysts.
- Malignant lesions of the lymph nodes and of the head and neck region: Possibilities that must be distinguished, particularly in a persistent adult neck lump, and the reason the guideline calls for a more cautious approach.
Each of these groups requires a different approach to investigation and treatment. The aim of assessment is to determine which structure the lump arises from and what its nature is, through a measured sequence of investigations.
What is done in the ENT and head-and-neck examination?
The assessment begins with a detailed history: when the lump was noticed, how fast it has grown, whether it is painful, accompanying fever and signs of infection, hoarseness, difficulty swallowing, ear pain, weight loss and night sweats, smoking and alcohol use, and previous illnesses and operations.
During the examination the location, size, consistency, mobility and tenderness of the lump and its relationship to the surrounding tissues are assessed. Examination of the mouth, throat, nose and larynx is an integral part of this, because the cause of an enlarged lymph node in the neck may lie in these areas. Where needed, the nose, nasopharynx and larynx are seen directly with a thin optical instrument (endoscopy).
Imaging and tissue sampling
The investigation is chosen according to the person’s age, the location of the lump, the examination findings and the risk profile; no single imaging test is mandatory for every neck lump.
Ultrasound of the neck, which involves no radiation, is highly useful in selected situations: lumps arising from the thyroid, lumps arising from the salivary glands, superficial lymph nodes and masses, and, where appropriate, ultrasound-guided fine-needle aspiration are the main examples.
For an adult neck lump considered to be at increased risk of malignancy, the AAO-HNSF guideline recommends contrast-enhanced CT or MRI to show the extent of the lump and its relationship to deep structures. Which method is chosen is decided by the physician according to the location of the lump, the likely cause and the examination findings.
When tissue diagnosis is required and the diagnosis remains uncertain, the guideline prefers fine-needle aspiration biopsy over surgical removal of the lump for examination; this is the sampling of cells with a thin needle, usually performed in the clinic in a short time and, where appropriate, under ultrasound guidance. Not every neck lump needs a biopsy; lymph nodes thought to be due to infection may be observed for a period determined by the physician.
Treatment and management approaches
Treatment is planned according to the cause of the lump; there is no single “neck lump treatment”.
In lymph node enlargement attributed to an infection, treatment is directed at the underlying infection; nodes that do not shrink within the observation period set by the physician are reassessed. For lumps found to arise from the thyroid or the salivary glands, follow-up and treatment are planned according to the findings specific to that organ and, where needed, further investigations. For some salivary gland lumps and developmental cysts, surgery may be one of the options; whether it is needed is decided from the definitive diagnosis, the features of the lump and the clinical assessment. Where clinically appropriate, the relevant specialties may take part in this process; that is not a fixed sequence applying to every lump. In lumps found to be malignant, treatment is determined within a plan in which the relevant specialties work together.
At every stage the findings and the options are discussed with the person concerned. This page deliberately contains no drug names, doses or individual treatment plans.
Frequently asked questions
Is the swelling I have noticed in my neck cancer?
This question cannot be answered without an examination. The possible causes of a neck lump include enlarged lymph nodes due to infection, lesions arising from the thyroid and salivary glands, and developmental cysts; malignant causes are also among the possibilities and cannot be distinguished from the outside. For that reason, particularly in an adult, a lump that has been present for two weeks or longer or cannot be explained by an infection should be assessed by examination. The assessment is carried out to determine the cause, not to confirm a fear.
How long can I wait?
Tender lymph node enlargement arising during a clear infection may settle together with the infection. The guideline recommends assessment without delay of an adult neck lump that cannot be explained by an infection, has been present for two weeks or longer, or whose duration is uncertain. If there is difficulty breathing, rapid growth, high fever or difficulty swallowing, there should be no waiting.
Is a biopsy painful or dangerous?
Fine-needle aspiration biopsy is an investigation in which cells are sampled with a thin needle; it is completed in the clinic in a short time and usually causes discomfort similar to having blood taken. Removing the lump for examination is a separate surgical decision and is considered only in specific situations. Which method is appropriate is decided by the physician according to the features of the lump.
Ultrasound or CT?
It depends on the lump. Ultrasound involves no radiation and is particularly useful for thyroid, salivary gland and superficial lumps; for an adult lump considered to be at increased risk of malignancy, the guideline recommends contrast-enhanced CT or MRI instead. No single imaging test is mandatory for every neck lump; the choice is made by the physician according to age, the location of the lump, the examination findings and the risk profile.