
PATIENT INFORMATION
Nasal Obstruction
Nasal obstruction is difficulty breathing through the nose, usually described as a blocked or stuffy nose; it may affect one or both sides and may be constant or intermittent. Its causes include inflammatory conditions of the nasal lining, a deviated septum, enlarged turbinates, sinusitis and nasal polyps, as well as temporary infections. The feeling of blockage does not by itself reveal the cause; the mechanism involved is determined by the history and examination. This page explains the common causes, how the ENT assessment is carried out and how the treatment approach is chosen.
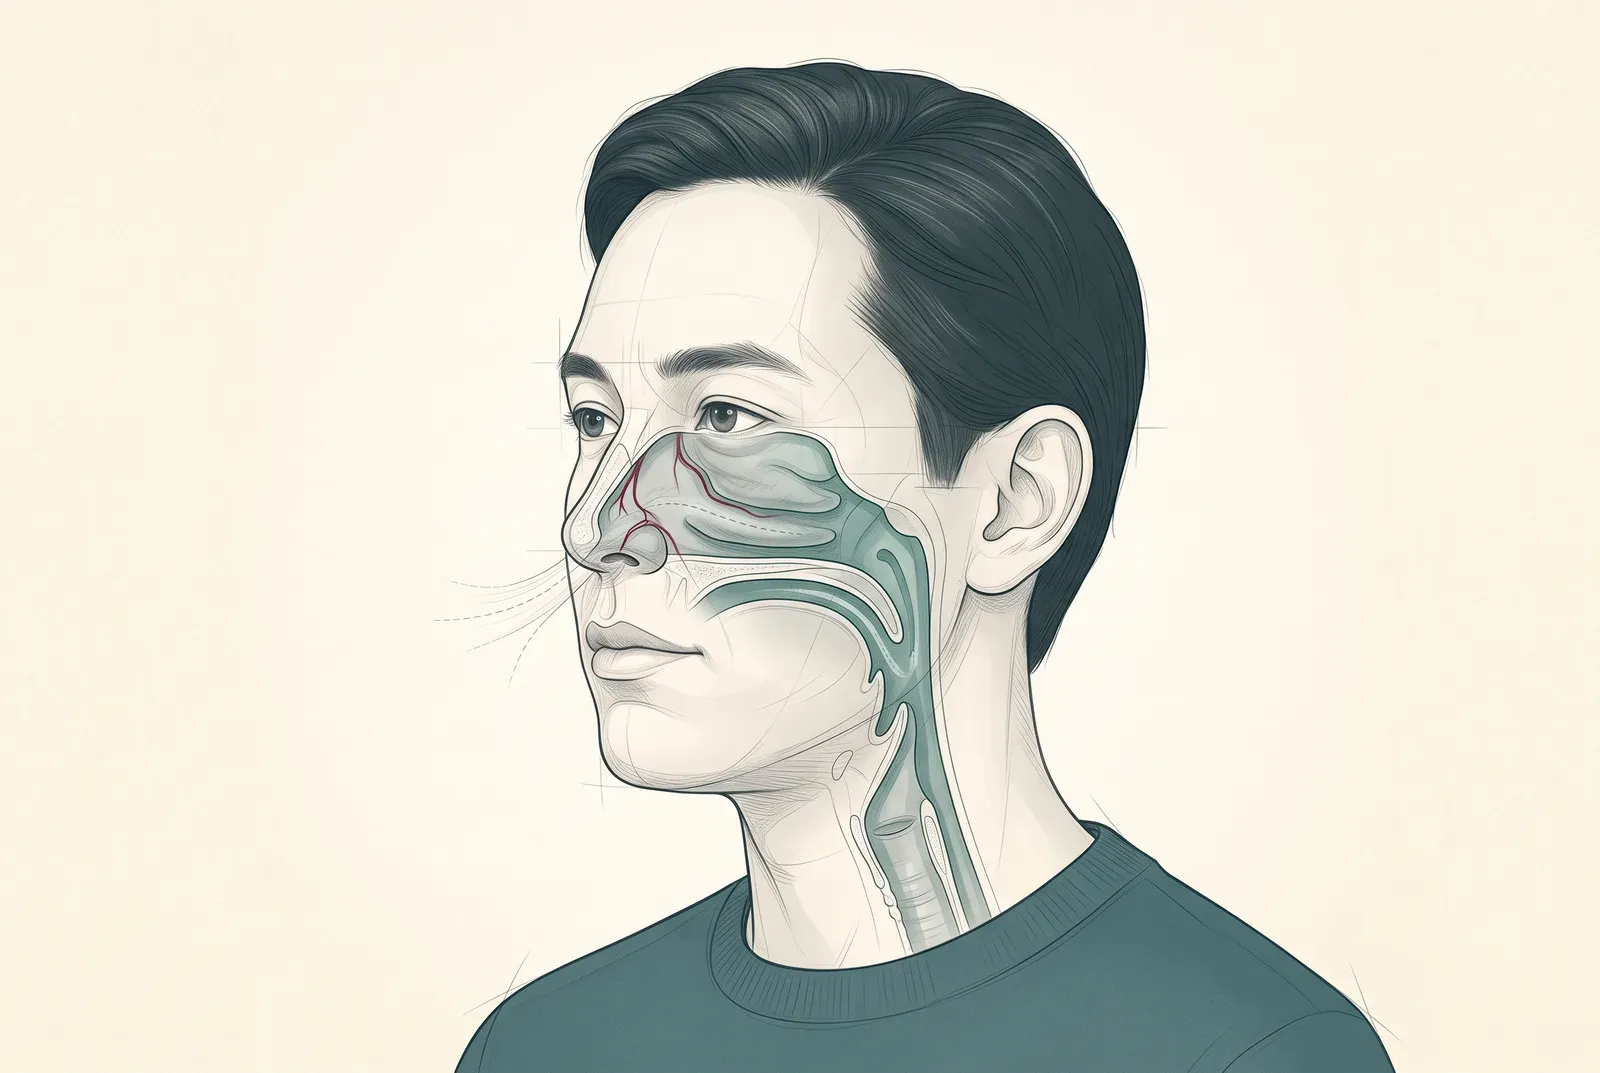
What is nasal obstruction?
Nasal obstruction is an impaired flow of air through the nose, or the feeling that this flow is inadequate. The complaint does not always mean the nose is completely closed; it is usually described as difficulty breathing through one or both sides.
The turbinates inside the nose swell and shrink alternately during the day. It is therefore normal, even in healthy people, for one side to feel more blocked than the other from time to time. What makes the complaint significant is that it becomes persistent, affects sleep and daily life, or continues stubbornly on one side.
The useful distinctions in assessment are these: is the obstruction on one side or both; constant or intermittent; related to seasons, changes of environment or allergic complaints; accompanied by nasal discharge, postnasal drip, a reduced sense of smell, facial pressure, nosebleeds, snoring or breathing difficulty during sleep; is there a history of nasal injury or nasal surgery; and which nasal sprays have been used, and for how long.
What are the most common causes?
The causes of nasal obstruction can broadly be grouped as inflammatory (mucosal) and structural; the common causes are:
- Rhinitis: Allergic and non-allergic rhinitis cause obstruction through swelling of the nasal lining; it is usually bilateral and may be accompanied by sneezing, discharge and itching.
- Septal deviation: A bend in the partition that separates the two sides of the nose; it usually causes a constant obstruction that is more marked on one side.
- Turbinate enlargement: Permanent enlargement of the turbinates inside the nose, often accompanying allergic and inflammatory conditions.
- Acute and chronic rhinosinusitis: Inflammation of the nasal and sinus lining; obstruction may be accompanied by discharge, facial pressure or a reduced sense of smell.
- Nasal polyps: Growths that develop as one form of chronic inflammatory disease, usually on both sides and associated with a reduced sense of smell.
- Upper respiratory infections: Temporary obstruction that arises with the common cold and similar illnesses and settles within days.
- Inappropriate long-term use of decongestant sprays: Using nasal decongestant sprays for longer than intended can make the obstruction worse when the spray is stopped.
- Rarer structural causes and growths inside the nose: Less common causes that should be considered, particularly in persistent one-sided presentations.
These causes frequently coexist; for example, a person with a deviated septum may also have allergic rhinitis, and the inflammatory component may be responsible for most of the complaint. The treatment plan is therefore based not on a single cause but on the combination of causes identified.
Why are one-sided and two-sided obstruction assessed differently?
Two-sided obstruction is more often related to mucosal, that is inflammatory, causes: allergic and non-allergic rhinitis, chronic rhinosinusitis and nasal polyps belong to this group.
In constant one-sided obstruction, structural causes come to the fore, particularly septal deviation. In addition, the range of possible causes of a persistent problem confined to one side differs from that of two-sided presentations; direct inspection of the inside of the nose therefore becomes more important.
This distinction is an assessment criterion, not a danger sign: septal deviation is one of the common structural causes of constant one-sided obstruction, and obstruction on one side does not in itself mean a serious disease.
What is done in the ENT assessment?
The assessment begins with a detailed history: the duration of the obstruction, whether it affects one or both sides, its variation during the day and across seasons, accompanying discharge, sneezing, reduced sense of smell, facial pressure, nosebleeds and sleep-related complaints; previous nasal injury or surgery; and the medicines and nasal sprays used.
During the examination the front of the nose is inspected with a light and a speculum; the position of the septum, the size of the turbinates, the appearance of the lining, and any discharge or polyps are assessed. Nasal endoscopy is performed where needed.
If the history suggests an allergic background, allergy assessment may be considered; allergy tests are not requested routinely for every patient and are meaningful when the history and examination findings point that way.
When might nasal endoscopy be needed?
Nasal endoscopy is the direct visualisation of the inside of the nose and its posterior parts with a thin optical instrument. It allows areas that cannot be seen at the front examination to be assessed.
Endoscopy is particularly useful when chronic rhinosinusitis or polyps are suspected, in persistent one-sided findings, and when surgery is being planned. Not every complaint of nasal obstruction requires endoscopy; if it is not performed, this does not mean the examination was incomplete. Whether it is needed is decided from the history and the initial examination findings.
Is imaging always necessary?
No. In simple, uncomplicated nasal obstruction, CT or MRI is not routinely required; guidelines do not make radiological imaging a condition for the diagnosis of chronic rhinosinusitis in primary care.
Imaging is meaningful when its result would change treatment: chronic rhinosinusitis that does not respond to appropriate medical treatment, surgical planning, unusual findings and presentations suggesting a growth inside the nose are the main examples.
CT is not needed to demonstrate a deviated septum; the septum and turbinates are assessed by examination.
How is the treatment approach decided?
Treatment is planned according to the mechanism underlying the obstruction; there is no single “nasal obstruction treatment”.
In inflammatory causes, treatment aims to reduce the swelling of the nasal lining. Saline nasal irrigation can be used as a supportive measure. In allergic rhinitis and chronic rhinosinusitis, intranasal corticosteroid treatment is the option that guidelines emphasise; where there is an allergic background, allergen avoidance and allergy-directed treatments are considered separately.
Inappropriate long-term use of decongestant sprays may be a factor that sustains or worsens the obstruction; where such use exists, addressing it is one of the first steps of treatment. Intranasal corticosteroid sprays and decongestant sprays are different medicines and are used differently.
In obstruction that persists despite appropriate medical treatment and is thought to be due to a structural cause, surgical options directed at the septum and turbinates may be considered. Surgery does not replace the treatment of inflammatory disease and is not necessary for every nasal obstruction; whether it is appropriate is decided by assessing the examination findings together with the response to treatment.
This page deliberately contains no drug names, doses or treatment durations; treatment is planned individually by the physician.
When is earlier assessment needed?
Nasal obstruction is usually not an emergency. Guidelines nevertheless recommend bringing the assessment forward and inspecting the inside of the nose more closely when certain findings are present:
- Persistent obstruction on one side only, or other one-sided nasal symptoms
- Recurrent or unexplained nosebleeds
- Marked crusting inside the nose
- A persistent bad smell
- Swelling or redness around the eye, forward displacement of the eye, double vision or reduced vision
- Severe, persistent one-sided headache or swelling over the forehead
- Facial numbness or other nervous-system symptoms
None of these findings on its own indicates a particular diagnosis. Because they change the range of possible causes, however, assessment should not be postponed and the inside of the nose should be inspected directly. Where symptoms involving the eye region, vision or the nervous system are present, medical assessment should take place without delay.
Frequently asked questions
Is one-sided nasal obstruction significant?
Septal deviation is one of the common structural causes of constant one-sided nasal obstruction, and one-sided obstruction does not in itself mean a serious disease. Because the range of possible causes differs when obstruction persists on one side, however, it is appropriate to assess the inside of the nose by examination and, if necessary, endoscopy; if bleeding, crusting or a bad smell is also present, that assessment is brought forward.
Does nasal obstruction mean I have a deviated septum?
No. Septal deviation is a common cause, but allergic and non-allergic rhinitis, turbinate enlargement, sinusitis and nasal polyps produce the same complaint. These causes can also coexist; finding a deviation does not mean that the whole complaint is due to it.
Is it safe to use a nasal spray?
Nasal sprays are not a single group. Intranasal corticosteroid sprays are treatment options that appear in guidelines for inflammatory conditions such as allergic rhinitis and chronic rhinosinusitis and are continued on a physician’s advice. Decongestant sprays give short-term relief; used inappropriately for long periods, they can make the obstruction worse. Which spray is used, and for how long, is decided by the physician.
Is a CT scan needed for every nasal obstruction?
No. The diagnosis is made primarily from the history and examination; CT is not needed to assess the septum and turbinates. Imaging is requested in situations where it would change the outcome, such as chronic rhinosinusitis that does not respond to appropriate treatment, surgical planning, or unusual findings suggesting a growth.